
Key points
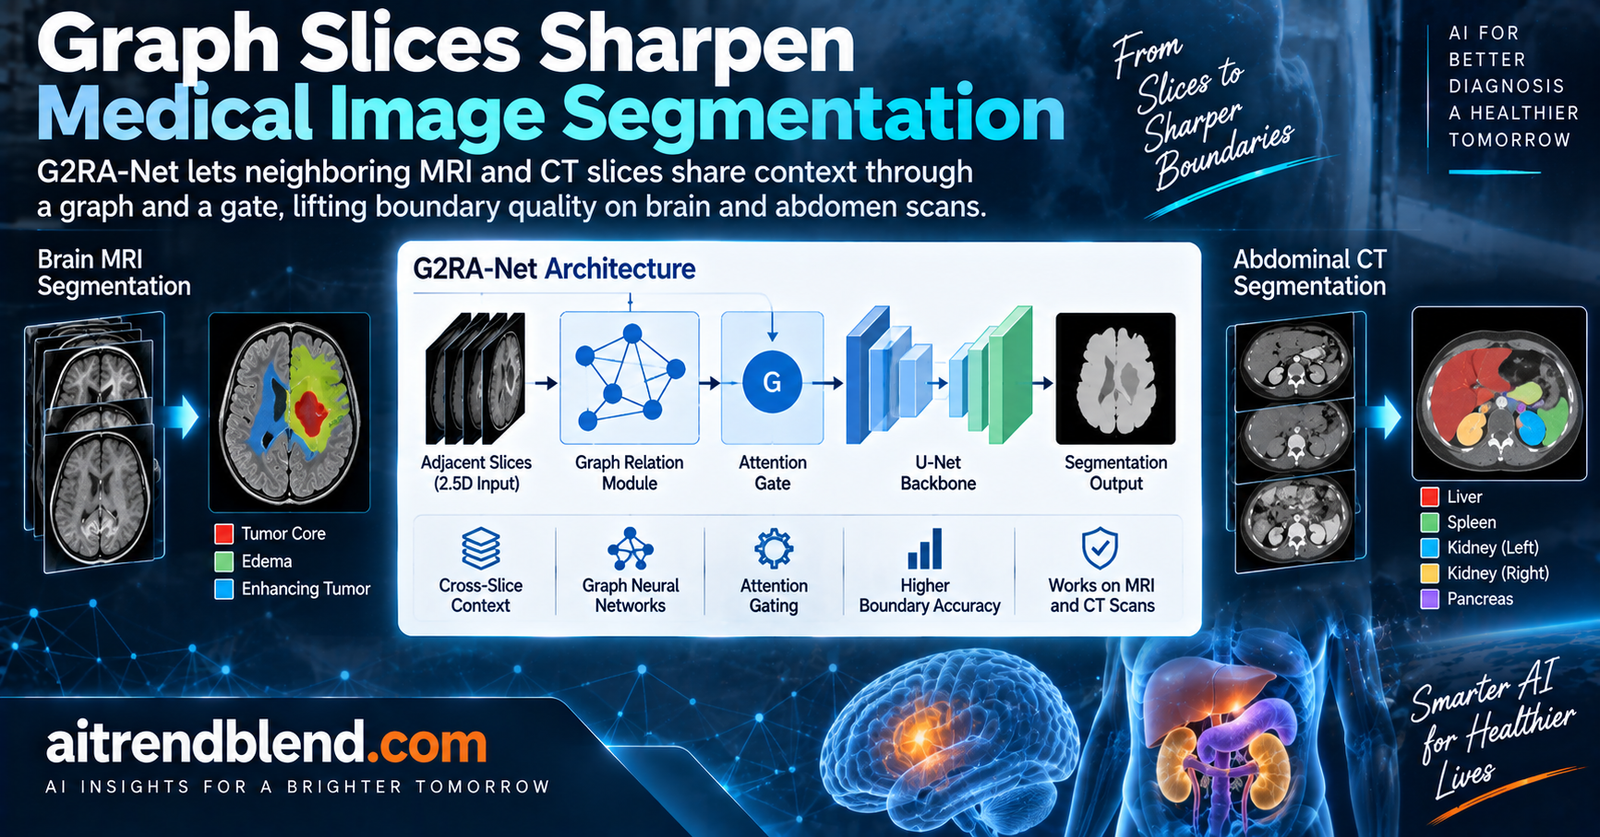
- G2RA-Net is a medical image segmentation framework that adds cross slice reasoning to a standard 2D U-Net without paying the full cost of a 3D model.
- Its first module treats a small group of consecutive slices as nodes in a graph and passes messages between them, so each slice inherits anatomical context from its neighbors.
- Its second module is a gate that learns which neighboring slices and which spatial regions actually matter, then suppresses the rest to reduce false responses.
- On brain MRI it reaches a Macro Dice of 0.8328 and on abdominal CT 0.7174, beating the strongest compared baselines on both overlap and boundary quality.
- The two modules help unevenly. The graph module gains more on brain scans, while the gate gains more on abdomen scans, which tells a useful story about where each idea pays off.
The problem, a scan is a stack, not a picture
Medical image segmentation is the task of coloring in a scan, drawing a precise outline around every organ or lesion so that a clinician can measure it, track it over time, or plan around it. Done by hand it is slow and tedious, and two experts rarely draw the exact same boundary. That is why deep learning has been chasing the problem for a decade, and why the humble U-Net, a network shaped like a funnel that compresses an image then reconstructs a labeled version of it, remains the workhorse of the field.
The trouble sits in the third dimension. A CT or MRI scan is a volume, a stack of two dimensional slices, and those slices are often spaced much farther apart than the pixels within each slice. That mismatch has a name, anisotropy, and it shapes every design choice that follows. A model has to decide how much to trust what it sees within a slice against what it can infer from the slices around it, and getting that balance wrong costs both accuracy and consistency.
Three ways to read a volume, and why each falls short
There are essentially three schools of thought, and the paper is a direct response to the weaknesses of all three. The first processes each slice on its own with a plain 2D network. This is fast and light and preserves the fine detail within a slice, but it is blind to the volume. An organ that fades in and out across slices confuses it, because it never sees the neighbors that would resolve the ambiguity.
The second builds a fully three dimensional network that consumes the whole volume at once. This captures the anatomical continuity the 2D approach misses, but it is expensive in computation and memory, and it struggles precisely when slices are far apart, which is the common case in real scans. The third, a middle path often called 2.5D, feeds a small stack of neighboring slices into a mostly 2D network and lets a cross slice attention mechanism mix them. This is the sweet spot the authors aim for, but they point out a real weakness. Not every neighboring slice is equally relevant, and naive attention can pull in misleading context, lighting up false responses where there should be none. What the middle path needs is not just cross slice mixing but selective cross slice mixing.
That is the gap G2RA-Net sets out to fill. Its full name, graph based cross slice relation modeling with attention gating, is a mouthful, but it names the two ideas cleanly. Model the relationships between slices explicitly with a graph, and then gate that shared context so only the useful parts survive.
The idea, let the slices talk to each other as a graph
Here is where it gets interesting. The team, led by Shengye Wang and Zonglin Wu at Southwest University with collaborators in London and Xiamen, keep the efficient 2D backbone and add their machinery at the points where it matters most. The first module lives at the bottleneck, the narrow waist of the U-Net where the image has been compressed to its most abstract form.
Slices as nodes, context as messages
The module is called Graph Based Slice Relationship Modeling, or GSRM, and its logic is elegant. Take the group of consecutive slices, and represent each one as a single node in a tiny graph. To turn a slice into a node, it pools the whole feature map down to one compact descriptor.
Now the slices are nodes, and an adjacency matrix describes how they connect. The design here is deliberate. The connections are fixed and weighted to encode a piece of anatomical common sense, that a slice is most related to its immediate neighbors, less related to distant ones, and also linked to a global summary node and to itself. That matrix is symmetrically normalized in the standard way graph networks do, so that message passing stays numerically stable.
Two lightweight graph propagation layers then let each node gather information from its neighbors, updating the slice descriptors so each one now carries a sense of its anatomical surroundings. The final touch is restraint. Rather than overwrite the spatial feature maps, GSRM uses the updated descriptors only as a gentle multiplier, a channel scaling factor centred on one.
That centring on one is the same stabilizing trick good architectures reach for again and again. When the graph has nothing useful to add, the multiplier stays near one and the features pass through unchanged. The spatial layout is never disturbed, so the model keeps its fine detail while gaining cross slice awareness. And because the graph has only a handful of nodes, one per slice in the group, the whole thing adds almost no computational cost. This is graph reasoning applied where it is cheap and skipped where it would be expensive.
A gate that decides which neighbors matter
Graph propagation at the bottleneck is a good start, but the bottleneck is only one point in the network. As the U-Net rebuilds the image through its decoder, it needs to keep making cross slice decisions at every scale. That is the job of the second module, the Cross Slice Attention Gate, or CSAG, and it runs at the bottleneck and at every decoder stage.
CSAG does its work in two passes. First it decides which channels to trust across slices, then it decides which spatial locations to trust within a slice. For the cross slice pass, it again pools each slice to a descriptor, then computes a familiar self attention over the slices, letting each slice weigh its relevance to every other.
The result is a content dependent gate that strengthens channels backed by semantically related slices and quiets the inconsistent ones. What makes the design distinctive is that this learned attention runs in parallel with a second, structural gate. The adjacency matrix from the graph is flattened and passed through a small network to produce its own gating vector, one that hard codes the prior that adjacent slices are more closely related. The two gates, one learned from content and one fixed by anatomy, combine as a residual modulation.
Only after that cross slice channel decision does the module turn inward, running two convolutions to produce a spatial attention map that highlights the task relevant regions within each slice and dampens the rest.
Placed after each skip connection and before the features are fused, the gate controls both the fine detail the skip connections carry and how that detail merges with the upsampled features. In plain terms, it is a filter that keeps asking, at every level of reconstruction, which of my neighbors should I actually believe right now.
The model does not just mix neighboring slices. It learns which neighbors to trust and which to ignore, which is exactly the discipline that naive cross slice attention lacks.A plain reading of the two module design
How it is trained and measured
Training pushes on three fronts at once through a combined loss. A cross entropy term handles the basic pixel by pixel classification, a Dice term rewards overlap between the prediction and the truth, and a Hausdorff distance transform term specifically punishes boundary errors, the places where an outline strays from where it should be.
The evaluation is unusually careful, and worth pausing on because it shapes how you should read the results. The authors lean on macro averaged scores, which give every organ class equal weight within a case and every case equal weight overall. This matters because pooled pixel level scores can flatter a model by letting large easy structures hide failures on small ones. Reporting Macro Dice and Macro IoU for overlap alongside Macro HD95 and Macro ASD for boundary error is a deliberately honest choice, since a model can score well on overlap while still drawing ragged edges.
Two public datasets from the Learn2Reg challenge anchor the experiments. The first is a brain MRI collection with 414 volumes and 35 labeled structures. The second is an abdominal CT collection with just 30 volumes and 13 labeled organs. The model reads three consecutive axial slices at a time, resized to 224 by 224, with CT intensities clipped to a window running from minus 175 to 250 Hounsfield units. Training runs for up to 100 epochs on a single consumer grade graphics card, which is a point in the method’s favor. It is not demanding hardware.
What the numbers show
On the brain MRI data, G2RA-Net reaches a Macro Dice of 0.8328 and a Macro IoU of 0.7603. Compared against the strongest baseline it beat there, a transformer based U-Net variant, those are gains of 0.84 and 1.70 percentage points on overlap, and the boundary metrics improve too, with the average surface distance dropping from 11.83 to 10.25. On the abdominal CT data it again comes out ahead of the strongest baseline it faced, a plain U-Net, lifting Macro Dice and reducing boundary error across the board.
The most informative results are the ablations, where the team adds one module at a time so you can see what each contributes. The story they tell is more interesting than the headline.
| Brain MRI (OASIS) | Macro Dice | Macro IoU | Macro HD95 | Macro ASD |
|---|---|---|---|---|
| U-Net baseline | 0.7884 | 0.7125 | 30.00 | 28.93 |
| U-Net plus graph module | 0.8194 | 0.7428 | 13.48 | 12.33 |
| Full G2RA-Net (both modules) | 0.8328 | 0.7603 | 12.43 | 10.25 |
Brain MRI ablation. Higher overlap is better, lower boundary distance is better. The graph module alone slashes boundary error from 30.00 to 13.48.
| Abdominal CT | Macro Dice | Macro IoU | Macro HD95 | Macro ASD |
|---|---|---|---|---|
| U-Net baseline | 0.6922 | 0.5673 | 9.49 | 1.96 |
| U-Net plus graph module | 0.6999 | 0.5709 | 9.41 | 1.95 |
| Full G2RA-Net (both modules) | 0.7174 | 0.5939 | 9.16 | 1.93 |
Abdominal CT ablation. Here the gate, added second, drives most of the gain rather than the graph module.
Reading the ablation, why brain and abdomen reward different modules
This is the part that rewards a close look. On the brain scans, the graph module does the heavy lifting. Adding it alone lifts Macro Dice by 3.10 percentage points and collapses the boundary error from 30.00 down to 13.48, an enormous jump, before the gate adds a smaller final polish. On the abdominal scans the order flips. The graph module barely moves the needle, and it is the gate, added second, that delivers the larger share of the improvement, with a Macro IoU gain of 2.30 percentage points against the graph module’s 0.36.
Why the reversal? The paper does not fully unpack it, so this is interpretation rather than proof, but the shapes of the two problems suggest an answer. Brain structures tend to vary smoothly and continuously from slice to slice, which is exactly the regularity a graph over neighboring slices is built to exploit. Abdominal organs are messier, they shift, deform, and appear or vanish more abruptly between slices, so a fixed graph prior helps less, and the flexible content aware gate that can decide case by case which neighbors to trust becomes the more valuable tool. Read that way, the two modules are not redundant. They are covering different failure modes, and a scan type that stresses one will lean on the other.
The clinical translation gap
It is worth being clear eyed about the distance between these results and a hospital. A Macro Dice of 0.83 on a research benchmark is a solid engineering result, but it is not the same thing as a tool a radiologist can rely on for a specific organ in a specific patient. Benchmark scores are averages over curated public datasets that were cleaned, labeled, and split under controlled conditions. Real clinical images arrive from many different scanners with different settings, different contrast protocols, different patient populations, and the occasional artifact or pathology the training data never contained.
A segmentation that is 95 percent correct by pixel count can still miss the one small structure that matters for a diagnosis, which is precisely why the authors emphasize macro averaging and boundary metrics rather than a single pooled number. Even so, no reader of this paper should conclude that the method is ready to measure a tumor or plan a treatment. It has not been tested prospectively, it has not been validated across sites, and it has not been reviewed by clinicians for the failure modes that matter in care. The gap between a benchmark leaderboard and a deployed clinical instrument is measured in years of regulatory work, external validation, and careful study of where the model breaks. This work is a step on the research side of that gap, and it should be read as one.
Honest limitations, including the clinical ones
The paper is a preprint that the authors note has been submitted to the IEEE for possible publication, which means it has not yet cleared peer review. That status alone is a reason to hold the results loosely.
The sample sizes deserve blunt attention. The abdominal CT experiment rests on just 30 volumes, split into 21 for training, 5 for validation, and only 4 for testing. Four test volumes is a very thin basis for any confident claim, and small differences between methods on such a set can easily reflect the luck of which patients landed in the test split rather than a real advantage. The brain dataset is far healthier at 414 volumes, but even there the model is evaluated on a single benchmark from a single source, so its behavior on scans from a different hospital or scanner remains unknown. Dataset bias is a live concern precisely because both collections are curated research sets rather than a representative slice of clinical reality.
Generalization is the open question the paper does not answer. There is no cross dataset test, no evaluation on out of distribution scans, and no analysis of how the fixed adjacency prior behaves when slice spacing changes. The method also inherits the constraints of its inputs. It reads three slices at a time, so context beyond that immediate window is not modeled, and the fixed graph structure encodes an assumption about slice relationships that may not hold for every anatomy or acquisition. None of this makes the work less interesting. It makes it a careful proof of concept whose next step is the external validation that turns a promising architecture into evidence. For readers who want to see how other groups wrestle with the same boundary quality and small structure problems, our coverage of RABR-Net refining the cell boundaries that Dice scores miss and of one model that segments the pancreas across both CT and MRI are useful neighbors, as is our look at segmenting single ventricle hearts from cine MRI.
The full method, in runnable PyTorch
The block below is a faithful, self contained reference implementation of the two modules and the loss, wrapped around a compact 2D U-Net backbone, with a smoke test on dummy volumetric tensors. It follows the architecture described in the paper. Read it as a teaching implementation you can run and extend rather than the authors’ exact code, which was not released publicly.
# G2RA-Net: graph-based cross-slice relation modeling with attention gating.
# GSRM at the bottleneck, CSAG at the bottleneck and every decoder stage,
# wrapped around a compact 2D U-Net. Input is a group of consecutive slices.
import torch
import torch.nn as nn
import torch.nn.functional as F

def double_conv(cin, cout):
    return nn.Sequential(
        nn.Conv2d(cin, cout, 3, padding=1, bias=False), nn.BatchNorm2d(cout), nn.ReLU(inplace=True),
        nn.Conv2d(cout, cout, 3, padding=1, bias=False), nn.BatchNorm2d(cout), nn.ReLU(inplace=True))

# ----------------------------------------------------------------------
# 1. Fixed weighted slice adjacency (adjacent, distant, global, self-loop)
# ----------------------------------------------------------------------
def build_adjacency(S, device):
    A = torch.zeros(S, S, device=device)
    for i in range(S):
        for j in range(S):
            if i == j:            A[i, j] = 1.0          # self loop
            elif abs(i - j) == 1: A[i, j] = 0.6          # immediate neighbor
            else:                A[i, j] = 0.2          # distant slice
    deg = A.sum(1)
    d_inv_sqrt = torch.diag(deg.clamp(min=1e-6).pow(-0.5))
    return d_inv_sqrt @ A @ d_inv_sqrt                # symmetric normalization

# ----------------------------------------------------------------------
# 2. GSRM: slice graph at the bottleneck -> residual channel modulation
# ----------------------------------------------------------------------
class GSRM(nn.Module):
    def __init__(self, C):
        super().__init__()
        self.g1 = nn.Linear(C, C); self.g2 = nn.Linear(C, C)

    def forward(self, x, S):
        # x: (B*S, C, H, W)  -> reshape to (B, S, C, H, W)
        BS, C, H, W = x.shape; B = BS // S
        xr = x.view(B, S, C, H, W)
        h = xr.mean(dim=(3, 4))                       # node features (B, S, C) via GAP
        A = build_adjacency(S, x.device)             # (S, S) normalized
        h = F.relu(self.g1(torch.einsum("st,btc->bsc", A, h)))   # propagation layer 1
        h = F.relu(self.g2(torch.einsum("st,btc->bsc", A, h)))   # propagation layer 2
        gate = 1.0 + h.view(B, S, C, 1, 1)             # residual, centred on 1
        return (xr * gate).view(BS, C, H, W)

# ----------------------------------------------------------------------
# 3. CSAG: cross-slice channel gate (attention + adjacency) then spatial
# ----------------------------------------------------------------------
class CSAG(nn.Module):
    def __init__(self, C, d=64):
        super().__init__()
        self.q = nn.Linear(C, d); self.k = nn.Linear(C, d); self.v = nn.Linear(C, d)
        self.back = nn.Linear(d, C)                   # attention -> channel gate
        self.adj_mlp = nn.Sequential(nn.Linear(1, 16), nn.ReLU(inplace=True), nn.Linear(16, C))
        self.spatial = nn.Sequential(nn.Conv2d(C, C // 2 + 1, 3, padding=1), nn.ReLU(inplace=True),
                                     nn.Conv2d(C // 2 + 1, 1, 3, padding=1))
        self.d = d

    def forward(self, x, S):
        BS, C, H, W = x.shape; B = BS // S
        xr = x.view(B, S, C, H, W)
        p = xr.mean(dim=(3, 4))                       # slice descriptors (B, S, C)
        Q, K, V = self.q(p), self.k(p), self.v(p)
        alpha = torch.softmax(Q @ K.transpose(1, 2) / (self.d ** 0.5), dim=-1)  # (B,S,S)
        g_att = self.back(alpha @ V)                  # content-dependent channel gate (B,S,C)
        A = build_adjacency(S, x.device).view(1, S, S, 1).expand(B, S, S, 1)
        g_adj = self.adj_mlp(A).mean(dim=2)          # adjacency-prior channel gate (B,S,C)
        gate = 1.0 + (g_att + g_adj).view(B, S, C, 1, 1)
        x_mod = (xr * gate).view(BS, C, H, W)         # channel modulation
        a_sp = torch.sigmoid(self.spatial(x_mod))     # spatial attention (B*S,1,H,W)
        return x_mod * a_sp

# ----------------------------------------------------------------------
# 4. 2D U-Net backbone with GSRM at the bottleneck and CSAG in the decoder
# ----------------------------------------------------------------------
class G2RANet(nn.Module):
    def __init__(self, in_ch=1, n_classes=14, ch=(32, 64, 128, 256)):
        super().__init__()
        self.e1 = double_conv(in_ch, ch[0]); self.e2 = double_conv(ch[0], ch[1])
        self.e3 = double_conv(ch[1], ch[2]); self.e4 = double_conv(ch[2], ch[3])
        self.pool = nn.MaxPool2d(2)
        self.gsrm = GSRM(ch[3]); self.csag_b = CSAG(ch[3])
        self.up = nn.ModuleList([nn.ConvTranspose2d(ch[i], ch[i - 1], 2, stride=2) for i in (3, 2, 1)])
        self.dec = nn.ModuleList([double_conv(ch[i], ch[i - 1]) for i in (3, 2, 1)])
        self.csag = nn.ModuleList([CSAG(ch[i - 1]) for i in (3, 2, 1)])
        self.head = nn.Conv2d(ch[0], n_classes, 1)

    def forward(self, x):
        # x: (B, S, 1, H, W) group of consecutive slices
        B, S = x.shape[0], x.shape[1]
        x = x.view(B * S, x.shape[2], x.shape[3], x.shape[4])
        s1 = self.e1(x); s2 = self.e2(self.pool(s1))
        s3 = self.e3(self.pool(s2)); s4 = self.e4(self.pool(s3))
        b = self.csag_b(self.gsrm(s4, S), S)          # bottleneck: graph then gate
        skips = [s3, s2, s1]
        for up, dec, gate, skip in zip(self.up, self.dec, self.csag, skips):
            b = up(b)
            b = torch.cat([b, skip], dim=1)            # skip concatenation
            b = gate(b, S)                            # CSAG before fusion
            b = dec(b)
        logits = self.head(b)                         # (B*S, n_classes, H, W)
        return logits.view(B, S, -1, logits.shape[-2], logits.shape[-1])

# ----------------------------------------------------------------------
# 5. Joint loss = cross-entropy + Dice + boundary (distance-transform) term
# ----------------------------------------------------------------------
def dice_loss(logits, target, eps=1.0):
    prob = torch.softmax(logits, dim=1)
    oh = F.one_hot(target, prob.shape[1]).permute(0, 3, 1, 2).float()
    inter = (prob * oh).sum(dim=(2, 3))
    union = prob.sum(dim=(2, 3)) + oh.sum(dim=(2, 3))
    return (1 - (2 * inter + eps) / (union + eps)).mean()

def boundary_loss(logits, target):
    # lightweight stand-in for the Hausdorff distance-transform term:
    # penalize disagreement weighted by distance to the label boundary
    prob = torch.softmax(logits, dim=1)
    oh = F.one_hot(target, prob.shape[1]).permute(0, 3, 1, 2).float()
    edge = F.max_pool2d(oh, 3, 1, 1) - oh              # crude boundary band
    return ((prob - oh).abs() * (1 + 5 * edge)).mean()

def joint_loss(logits, target, lambdas=(1.0, 1.0, 0.5)):
    B, S, Cn, H, W = logits.shape
    lo = logits.reshape(B * S, Cn, H, W); tg = target.reshape(B * S, H, W)
    l1, l2, l3 = lambdas
    return (l1 * F.cross_entropy(lo, tg)
            + l2 * dice_loss(lo, tg)
            + l3 * boundary_loss(lo, tg))

# ----------------------------------------------------------------------
# 6. Smoke test on dummy data
# ----------------------------------------------------------------------
if __name__ == "__main__":
    B, S, H, W, n_cls = 2, 3, 64, 64, 14
    net = G2RANet(in_ch=1, n_classes=n_cls)
    x = torch.randn(B, S, 1, H, W)                     # 3 consecutive slices
    y = torch.randint(0, n_cls, (B, S, H, W))
    logits = net(x)
    print("logits:", logits.shape)                    # (2, 3, 14, 64, 64)
    print("loss:", float(joint_loss(logits, y)))
    print("params:", sum(p.numel() for p in net.parameters()), "| smoke test ok")
Conclusion
The central contribution of G2RA-Net is a clean answer to a stubborn question in medical image segmentation. How do you give a fast, cheap 2D network the volumetric awareness of a 3D one without paying the 3D price? The answer here is to model the relationships between neighboring slices explicitly, first as a graph that shares context at the bottleneck, then as a gate that keeps deciding, at every scale of reconstruction, which of that shared context to actually use. Both modules touch only the compact channel descriptors rather than the full spatial maps, so the volumetric reasoning stays cheap while the fine detail stays intact.
The conceptual heart of the work is selectivity. Earlier 2.5D methods showed that mixing neighboring slices helps, but they mixed indiscriminately, and indiscriminate mixing pulls in noise. By pairing a fixed anatomical prior with a learned content aware gate, the authors give the model a way to lean on structure when the anatomy is regular and on flexibility when it is not. The uneven ablation results, where the graph module dominates on brain scans and the gate dominates on abdomen scans, are the clearest evidence that this dual design is doing real and complementary work rather than stacking two versions of the same idea.
What makes the paper trustworthy is the restraint in its evaluation. Choosing macro averaged overlap and boundary metrics over a single flattering pooled score is the kind of methodological honesty that the medical imaging community has been pushing toward, because it refuses to let large easy organs hide failures on the small hard ones. The consistent improvement across overlap, pixel agreement, and boundary quality is a more convincing signal than any one number would be.
The honest limitations are significant and the paper does not fully resolve them. It is a preprint awaiting peer review. The abdominal result rests on four test volumes, which is far too few to support a strong claim. There is no cross site or out of distribution testing, and the fixed graph prior encodes an assumption about slice relationships that has not been stressed across different acquisitions. Between a benchmark score and a clinical tool lies a long road of external validation, regulatory scrutiny, and study of failure modes, and nothing in this work shortens that road. It earns its place on the research side of the gap, not the clinical side.
Read as a deployable system, this is not one, and the disclaimer at the top of this article is not a formality. Read as a design idea, which is whether explicit graph reasoning plus selective gating can lift a 2D backbone toward volumetric quality at low cost, it offers a careful and mostly persuasive yes, along with a genuinely useful insight into when each half of the idea matters most. For a field crowded with U-Net variants that all claim a fraction of a Dice point, a paper that also explains why its pieces help unevenly is a welcome kind of contribution.
Frequently asked questions
What does G2RA-Net actually do?
It segments medical scans, meaning it draws precise outlines around organs and structures in brain MRI and abdominal CT volumes. Its novelty is letting neighboring slices in a scan share context through a small graph and a learned gate, which improves both the overlap accuracy and the boundary quality of the outlines.
Why not just use a full 3D model?
Fully three dimensional networks capture volumetric context but are expensive in computation and memory and struggle when slices are spaced far apart, which is common in real scans. G2RA-Net keeps an efficient 2D backbone and adds lightweight cross slice reasoning only where it is cheap, at the compressed feature descriptors rather than the full image.
How good are the reported results?
On brain MRI it reached a Macro Dice of 0.8328 and on abdominal CT 0.7174, beating the strongest baselines it was compared against on both overlap and boundary metrics. These are research benchmark scores on public datasets, not measures of clinical performance, and the abdominal figure rests on only four test volumes.
Why do the two modules help different scans differently?
The graph module contributes most on brain scans, where anatomy varies smoothly across slices and a structural prior fits well. The gate contributes most on abdominal scans, where organs shift and change more abruptly, so a flexible module that decides case by case which neighbors to trust becomes more valuable. The two cover different failure modes.
Is this ready to use in a hospital?
No. It is a research preprint that has not been peer reviewed, validated across multiple sites, or cleared for clinical use. It has not been tested prospectively, and its abdominal evaluation uses a very small sample. It is a promising architecture on the research side of a long path toward clinical deployment.
What are the biggest weaknesses to keep in mind?
The abdominal CT test set is only four volumes, both datasets come from single curated sources with no cross site testing, and the fixed slice graph encodes an assumption about slice relationships that was not stressed under different scan settings. Generalization to real clinical images from other scanners remains unproven.
Read the source research
This analysis is based on the preprint by Shengye Wang, Zonglin Wu, Liang Fan, Yule Xue, and Haozhe Zhao. Go to the original for the full experimental detail and figures.
Citation. Wang, S., Wu, Z., Fan, L., Xue, Y., and Zhao, H. G2RA-Net, Graph-Based Cross-Slice Relation Modeling with Attention Gating for Medical Image Segmentation. arXiv preprint arXiv:2609.20088 (2026). Datasets are L2R-OASIS and L2R-Abdomen CT from the Learn2Reg challenge. This analysis is based on the published paper and an independent evaluation of its claims, and is not medical advice.